


Macular Atrophy: The Biology, Risk Factors, and Emerging Treatments for Central Vision Loss
Key Facts: Genetic Testing for Macular Atrophy Risk
- Sample Required: Blood or Saliva
- Fasting Rules: Not required
- Turnaround Time (TAT): 7-10 business days
- Base Cost: [Insert Current 2026 Price]
Written by: [Author Name] | Medically Reviewed by: [Reviewer Name] | Last Updated: [Date]
Understanding Macular Atrophy: Beyond the Basics of Vision Loss
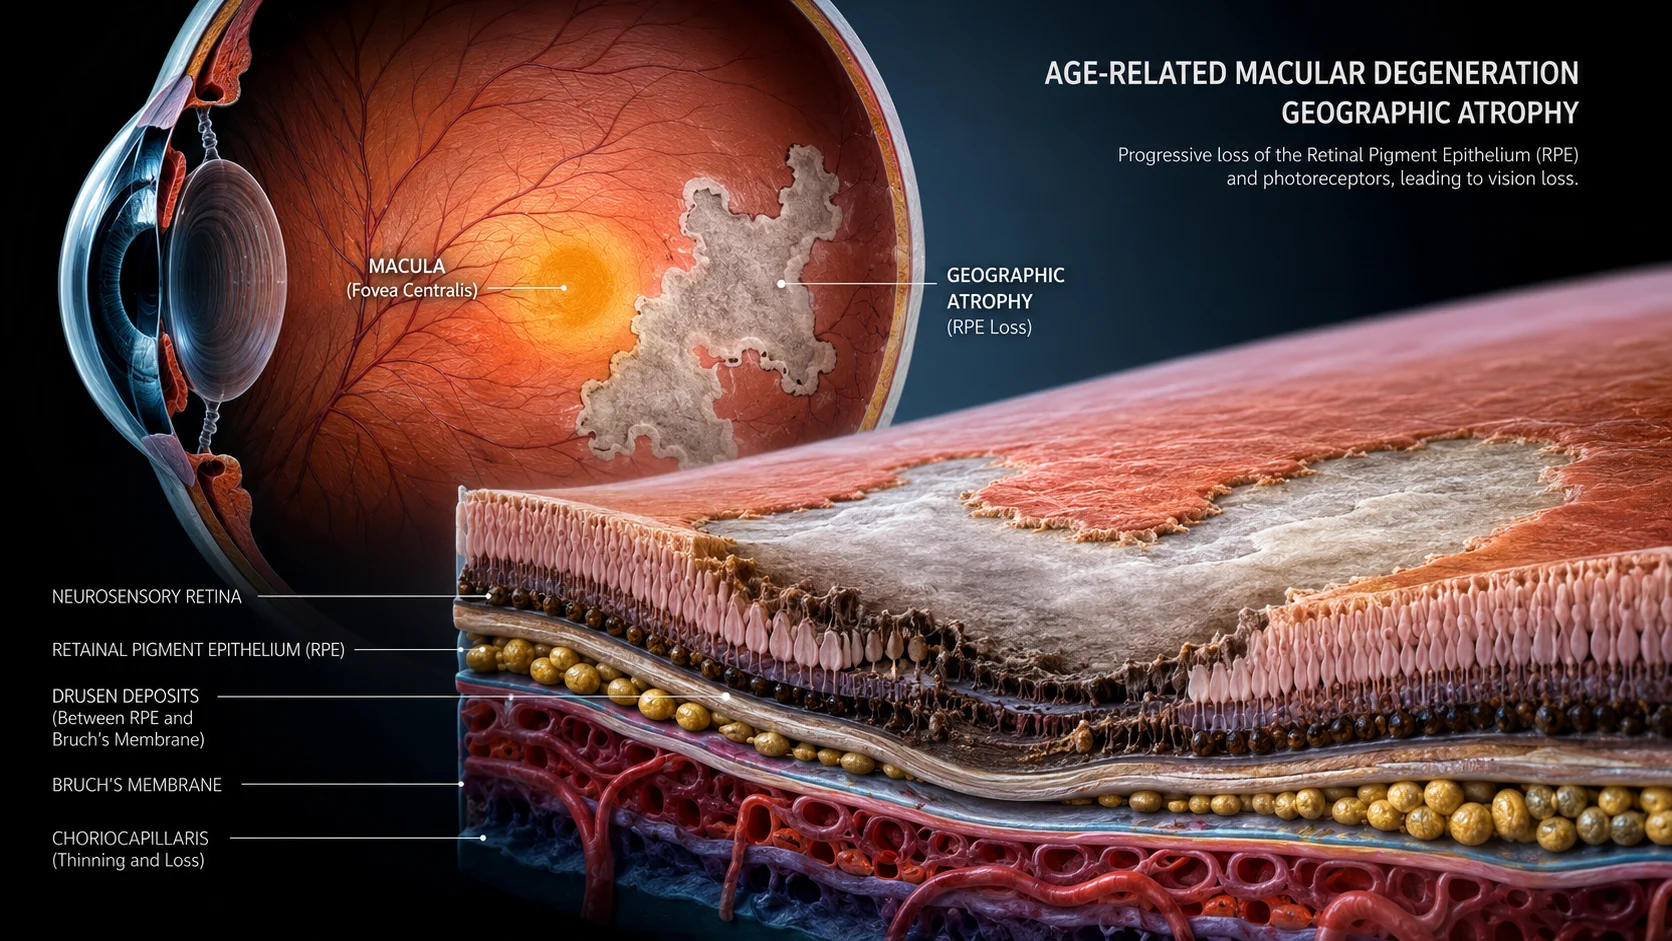
Macular atrophy is the progressive and irreversible loss of cells in the macula—the central part of the retina responsible for sharp, detailed vision. It represents the advanced stage of age-related macular degeneration (AMD), leading to permanent impairment of activities like reading, driving, and recognizing faces.
Globally, an estimated 196 million people are affected by AMD, with the prevalence of late-stage disease (including geographic atrophy) increasing exponentially with age. The impact is profound: 67% of patients with geographic atrophy become ineligible to drive within a median of 1.6 years based on visual acuity alone.
Pathophysiology of Macular Atrophy
The macula is the central region of the retina that enables fine detail vision. Macular atrophy occurs when the retinal pigment epithelium (RPE)—a supportive layer beneath the photoreceptors—deteriorates and dies, leading to progressive loss of photoreceptors and the underlying choriocapillaris in well-defined patches.
The term "geographic atrophy" is often used interchangeably with macular atrophy, referring to the late stage of dry AMD. The "geographic" descriptor comes from the map-like appearance of atrophic lesions that expand over time.
Drusen: The Warning Signs
The onset of macular atrophy is typically preceded by the accumulation of drusen—lipid-rich extracellular deposits beneath the retina. These yellow deposits are detectable during routine eye exams and are classified by size:
- Grade 1 (Early AMD): Few drusen deposits smaller than 63 µm
- Grade 2-3 (Intermediate AMD): Drusen between 63-124 µm
- Grade 4 (Geographic Atrophy): Drusen >125 µm with distinct areas of RPE and photoreceptor loss
Two Distinct Pathways to Atrophy
Recent clinical research has revealed that macular atrophy can develop through two separate pathways, even in patients receiving treatment.
Pathway 1: Neovascular-Related Atrophy
This pathway is associated with the development and exudation of macular neovascularization (MNV)—abnormal blood vessel growth commonly seen in wet AMD. Causes include:
- Physical harm from Type 3 neovessels
- Collapse of serous pigment epithelium detachment
- Fibrosis (scar tissue formation)
Pathway 2: Non-Neovascular Atrophy
This pathway involves lesions unrelated to neovascularization, primarily:
- Drusen accumulation
- Subretinal drusenoid deposits (reticular pseudodrusen)
| Feature | Neovascular-Related | Non-Neovascular |
|---|---|---|
| Primary Trigger | MNV, exudation, fibrosis | Drusen, reticular pseudodrusen |
| Clinical Context | Often seen after anti-VEGF therapy | Progression of dry AMD |
| Prevalence in Type 3 MNV | 92.7% after 12 months | Variable |
Epidemiology and Risk Factors
Macular atrophy affects diverse populations differently, with important implications for Indian patients.
Prevalence Among Asian Populations
A pooled analysis from the Asian Eye Epidemiology Consortium, including data from rural India, found the prevalence of myopic macular degeneration (MMD)—which includes macular atrophy—to be 0.4% among Asians in rural India. This compares to:
- 0.5% in Beijing, China
- 1.5% in Russia
- 5.2% in Singapore
The Central India Eye and Medical Study (2006), involving 4,561 participants over age 30, reported a macular atrophy prevalence of 0.2%.
Key Risk Factors for Asian Populations
- Older age (per year; OR=1.13)
- Female sex (OR=2.0)
- Myopia severity (per negative diopter; OR=1.7)
- Longer axial length (per mm; OR=3.1)
- Lower education (OR=1.9)
Clinical Presentation and Symptoms
Macular atrophy typically develops gradually, with symptoms becoming more pronounced as the fovea becomes involved.
Common Symptoms
- Loss of central vision acuity: Difficulty reading, recognizing faces, or performing detailed tasks
- Dark spots or scotomas: Blind spots in the central field of vision
- Difficulty in dim light: Needing brighter illumination for everyday activities
- Duller color perception: Colors appearing less vibrant or faded
The Silent Progression
Early macular atrophy may be asymptomatic, particularly if it begins in one eye or spares the fovea (a phenomenon known as "foveal sparing"). The atrophic patches typically appear in the perifoveal macula initially and expand over 1.5 to 2.4 years to involve the fovea.
| Symptom | Early Stage | Late Stage |
|---|---|---|
| Visual Acuity | Mild blurring | Severe loss |
| Scotomas | May be absent | Central blind spots |
| Color Perception | Slight dulling | Significant fading |
Diagnostic Modalities
Early detection is critical for managing macular atrophy and preserving vision. Diagnosis involves a comprehensive eye examination and advanced imaging techniques.
Key Diagnostic Tools
- Fundus Autofluorescence (FAF): Detects lipofuscin accumulation; areas of atrophy appear as reduced autofluorescence.
- Optical Coherence Tomography (OCT): High-resolution cross-sectional images to visualize retinal layers and detect structural changes.
- Color Fundus Photography: Two-dimensional images to visualize drusen, pigment changes, and atrophy.
- Microperimetry: Assesses macular sensitivity by projecting light stimuli onto different retinal points.
| Imaging Modality | What It Detects | Clinical Utility |
|---|---|---|
| FAF | Lipofuscin distribution | Identifies atrophic areas |
| OCT | Retinal layer structure | Early RPE/photoreceptor loss |
| Color Fundus | Drusen, pigment changes | Baseline documentation |
| Microperimetry | Retinal sensitivity | Functional mapping |
The Importance of Comprehensive Assessment
While visual acuity testing is important, it does not fully capture the patient's visual experience. A comprehensive assessment should combine:
- Best corrected visual acuity (BCVA)
- Low-luminance visual acuity (LLVA)
- Microperimetry
- Reading speed tests
Treatment and Management Strategies
Recent years have brought significant advances in macular atrophy treatment, though a cure remains elusive.
FDA-Approved Treatments
Two complement inhibitor therapies have been approved to slow disease progression:
Pegcetacoplan (SYFOVRE™) and avacincaptad pegol (IZERVAY™) are administered as intraocular injections monthly or every other month. These medications target the complement cascade—a part of the immune system implicated in the inflammatory processes driving AMD progression.
While these treatments show promising results in reducing lesion growth, they do not reverse existing damage and carry safety considerations.
Supportive Therapies
- AREDS2 Supplements: A specific combination of antioxidants (lutein, zeaxanthin, vitamin C, vitamin E, zinc, and copper) may slow progression in some patients.
- Visual Rehabilitation: Low-vision aids, special eyewear, and magnifying glasses can help maintain independence.
- Implantable Miniature Telescope (IMT): A surgical option that magnifies central vision and focuses it on healthy areas of the retina.
Clinical Trials and Emerging Approaches
Numerous clinical trials are exploring new therapeutic strategies, including:
- Anti-inflammatory therapies
- Neuroprotective agents
- Lipofuscin and visual cycle inhibitors
- Choroidal blood flow restoration
- Gene therapy
Genetic Testing and Risk Assessment
Genetic predisposition plays a significant role in the development of AMD and macular atrophy. DNA Labs India offers comprehensive genetic testing to identify risk variants associated with AMD, enabling early intervention and personalized management.
Our ISO 9001 certified lab uses advanced next-generation sequencing (NGS) to analyze key genes such as CFH, ARMS2, HTRA1, and others. This test helps individuals with a family history of AMD understand their risk and take proactive steps.
For more information on genetic testing for macular atrophy risk, contact DNA Labs India.
Lifestyle Modifications: Reducing Your Risk
While macular atrophy cannot be entirely prevented, addressing modifiable risk factors can reduce your likelihood of developing the condition.
Key Lifestyle Recommendations
- Quit smoking: Smoking is a major modifiable risk factor for AMD and macular atrophy.
- Manage chronic conditions: Control diabetes, high blood pressure, high cholesterol, and obesity.
- Protect your eyes: Wear sunglasses with yellow tint for sun protection; use safety eyewear for work and sports.
- Eat a healthy diet: Consume dark green leafy vegetables and foods rich in antioxidants.
- Regular eye exams: Annual comprehensive eye examinations are essential for those over 50.
When to See an Eye Specialist
Prompt evaluation is crucial if you experience:
- Blurred or distorted central vision
- Difficulty reading, recognizing faces, or driving
- Dark spots or blind spots in your central vision