


Thalassemia & Sickle Cell Premarital Screening: A Complete Guide for Indian Couples
At a Glance
- Sample Required: Blood sample (EDTA whole blood)
- Fasting Rules: No fasting required
- Turnaround Time (TAT): 3–5 working days
- Base Cost: ₹[Insert Current 2026 Price]
Why a Simple Blood Test Before Marriage Could Change Your Family's Future
Every year in India, thousands of couples find out—only after their child is born—that they are both carriers of the same inherited blood disorder. Neither partner was ever sick a day in their life. Neither had any reason to suspect anything was wrong. And yet, when two carriers of thalassemia or sickle cell disease have children together, the outcome can be a lifetime of transfusions, hospital visits, and medical uncertainty for that child.
This is one of the rare situations in medicine where the disease is almost entirely preventable—not through treatment, but through timing. A single blood test, taken before marriage or before pregnancy, can tell a couple everything they need to know to make an informed choice. This guide explains the biology, the numbers specific to India, and where the science of screening and treatment stands today.
What Thalassemia and Sickle Cell Disease Actually Are
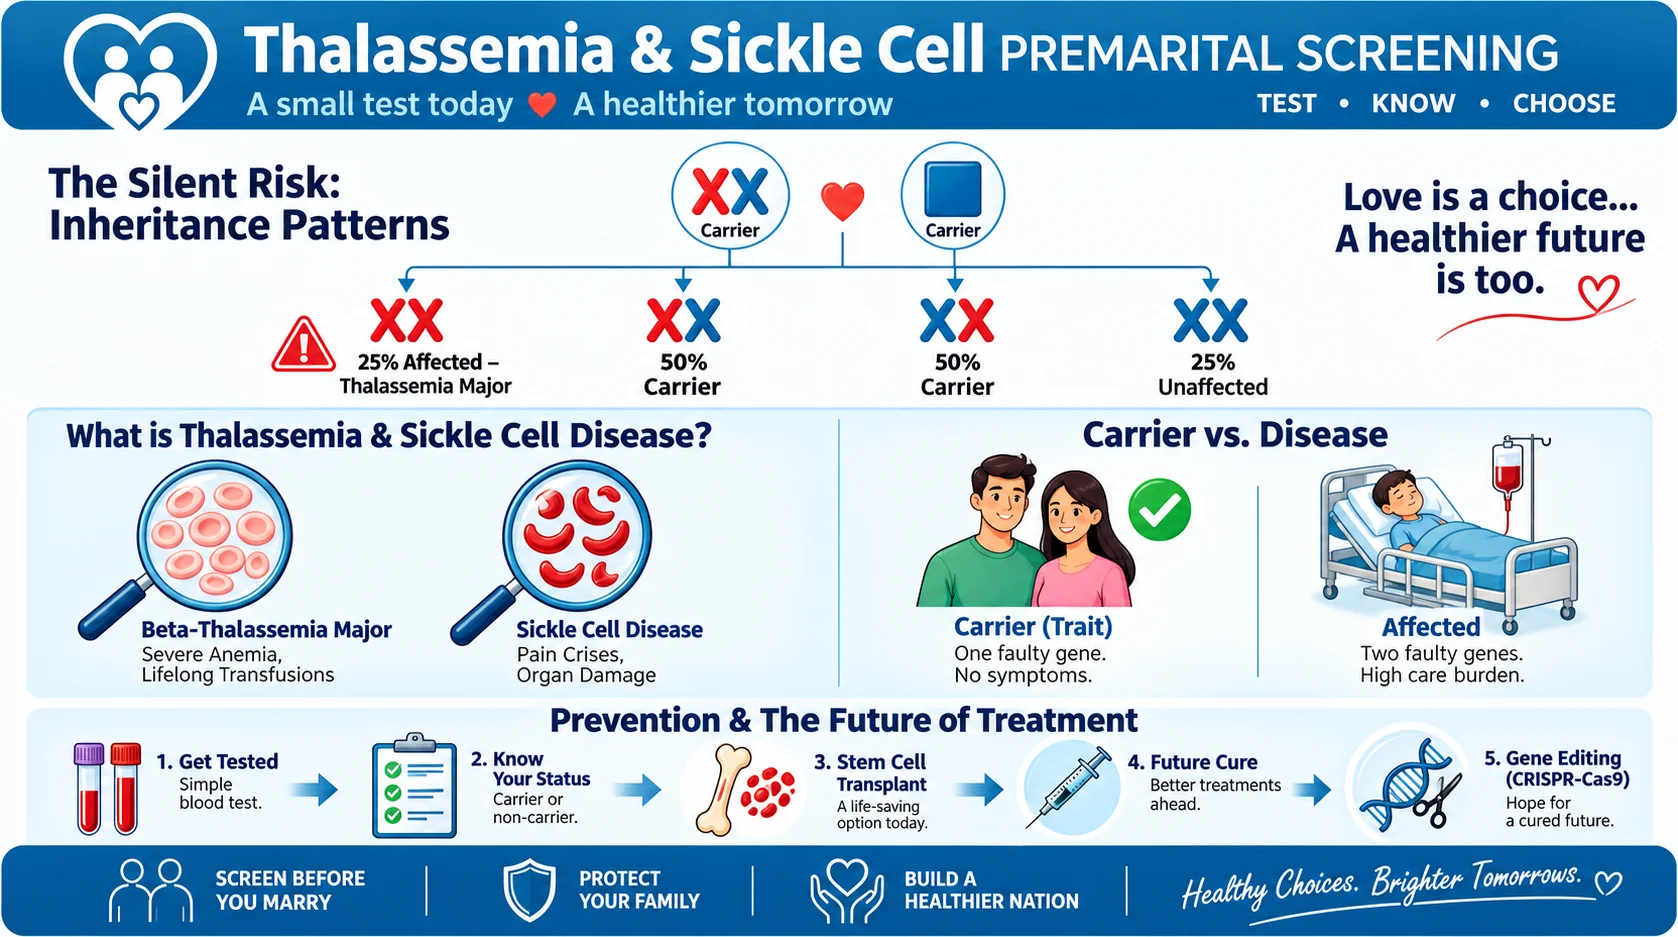
Both conditions are inherited hemoglobin disorders, meaning they affect the protein inside red blood cells that carries oxygen. Both are recessive, which is the detail that makes premarital screening so powerful: a person needs to inherit the faulty gene from both parents to develop the disease. Inheriting it from only one parent makes a person a carrier (also called having the "trait" or being a "minor")—healthy, symptom-free, and often completely unaware of their genetic status for their entire life.
Beta-Thalassemia: Minor vs. Major
Beta-thalassemia occurs when the body produces too little of one of the protein chains that make up healthy hemoglobin.
- Thalassemia minor (trait): One faulty gene copy. Usually no symptoms, sometimes mild anemia that's easy to mistake for iron deficiency.
- Thalassemia major: Two faulty gene copies. Presents in early childhood with severe anemia and requires regular blood transfusions and iron-chelation therapy for life, unless cured through stem cell or gene therapy.
Alpha-Thalassemia
Alpha-thalassemia works on a sliding scale depending on how many of the four alpha-globin genes are affected—from a silent carrier state with no symptoms at all, to Hemoglobin H disease, to the most severe form (Hb Bart's hydrops fetalis), which is incompatible with life. This gradient is part of why genetic confirmation matters more than a basic blood count alone.
Sickle Cell Trait vs. Sickle Cell Disease
Sickle cell disease is caused by a single mutation in the gene that codes for hemoglobin, which makes red blood cells stiffen into a crescent ("sickle") shape under low-oxygen conditions. These misshapen cells block small blood vessels, causing intensely painful episodes called vaso-occlusive crises, chronic anemia, and organ damage over time. A person with sickle cell trait (one copy of the gene) is generally healthy; a person with sickle cell disease (two copies, or one copy paired with another hemoglobin variant) faces a serious lifelong condition.
Why India Carries a Uniquely High Global Burden
India has more children living with thalassemia major than any other country in the world—current estimates put the number at around 150,000, with roughly 10,000 to 15,000 new babies born with the condition every year. Layered on top of that is a carrier pool of tens of millions of people who are silently unaffected but capable of passing the gene forward.
What makes the Indian picture particularly complex is how unevenly the carrier rate is distributed. While the national average sits around 3–4%, certain communities carry the trait at far higher frequencies—historically documented as elevated among groups including Sindhis, Punjabis, Gujaratis, Bengalis, and several Maharashtrian communities, among others. Even within a single state, carrier frequency can vary sharply from one district to the next, which is part of why blanket, one-size-fits-all screening assumptions don't work well here.
Sickle cell disease follows its own distinct geography—it disproportionately affects India's tribal populations, particularly in central-India states, which is precisely why national elimination efforts have specifically targeted these communities (more on this below).
The Math That Matters: What Happens When Two Carriers Marry
This is the single most important number in this entire topic, and it's worth spelling out plainly:
- If one partner is a carrier and the other is not: children face no risk of the disease itself (though some may be carriers).
- If both partners are carriers of the same disorder: each pregnancy carries a 25% chance of the child having the full disease, a 50% chance of the child being a carrier, and a 25% chance of the child being unaffected entirely.
That 25% figure doesn't change with each subsequent pregnancy—it resets every time. This is exactly why genetic counseling before conception (not after a diagnosis) is the single highest-leverage intervention available for these conditions.
The Silent Barrier: Why Screening Doesn't Always Translate to Prevention
If the test exists and the math is this clear, why does India still see thousands of new cases every year? The honest answer is cultural, not scientific. In many communities, families are hesitant to disclose that a son or daughter is a carrier, out of concern it will hurt their marriage prospects—even though carrier status has zero impact on a person's own health. This silence means that couples frequently never learn they're both carriers until they've already had an affected child.
Reframing carrier status as a routine, common, and non-stigmatizing genetic trait—rather than a hidden flaw—is arguably as important as the test itself in shifting outcomes.
Where India's Screening Policy Stands Today
Screening for these disorders in India isn't new, but the scale of the current push is. The National Sickle Cell Anemia Elimination Mission, launched in 2023, has set an ambitious goal: eliminating sickle cell disease as a public health problem by 2047. Progress so far has been substantial—over six crore people have been screened nationally, identifying more than two lakh people living with the disease and over sixteen lakh carriers, with states like Madhya Pradesh, Gujarat, Rajasthan, Telangana, Karnataka, and Uttarakhand posting the strongest screening coverage.
Momentum is also building around premarital screening specifically. Through 2026, patient advocacy groups such as the Thalassemia and Sickle Cell Society of India have been pushing state governments to make screening mandatory for young adults, framing it explicitly as a preventable public health issue rather than purely a treatment challenge.
It's worth being precise about where things currently stand: India does not yet have a nationwide mandatory premarital screening law of the kind seen in some Gulf countries. Screening today operates through national missions, state pilot programs, and individual choice—not legal requirement. That may change, but for now, acting on it is still a personal and family decision rather than a legal one.
The Treatment Frontier: From Lifelong Management to One-Time Cures
For decades, the only options for someone born with thalassemia major or sickle cell disease were regular blood transfusions, medication to manage iron overload, or a bone marrow transplant—itself only possible with a matched donor. That picture is now changing quickly.
Casgevy: The First CRISPR Gene-Editing Therapy
Casgevy (exagamglogene autotemcel) became the first CRISPR-based gene-editing therapy ever approved for human use, initially cleared for sickle cell disease and shortly after for transfusion-dependent beta-thalassemia. The treatment works by extracting a patient's own stem cells, editing them to switch the body back to producing fetal hemoglobin (a form that doesn't sickle), and reinfusing them—effectively addressing the disease at its genetic root rather than managing its symptoms. Approval has since expanded to children as young as two years old. The therapy remains extremely expensive and is not yet accessible to most patients in India, but it represents a genuine proof of concept that these diseases are curable, not just manageable.
BIRSA 101: India's Own Indigenous Gene Therapy
This is the development most Indian readers haven't heard about yet, and it's directly relevant to the country's tribal population most affected by sickle cell disease. In November 2025, India's Department of Science & Technology unveiled the country's first indigenous CRISPR-based gene therapy for sickle cell disease, named BIRSA 101 in honor of tribal freedom fighter Birsa Munda. The program is a collaboration between CSIR's Institute of Genomics and Integrative Biology, the Serum Institute of India, and AIIMS Delhi, with trial participants drawn from Madhya Pradesh, Chhattisgarh, and Jharkhand—the states carrying the heaviest tribal sickle cell burden.
As of mid-2026, the program has moved through Phase 2/3 clinical trial infrastructure, with a dedicated GMP manufacturing facility now in place and regulatory review anticipated in 2026–2027. If it clears approval, it would mark India's first domestically developed, and presumably far more affordable, curative option for a disease that has historically only offered lifelong management.
Information Gain: Carrier vs. Disease State
| Feature | Carrier (Trait) | Affected (Disease) |
|---|---|---|
| Genetic Status | One mutated gene copy | Two mutated gene copies (or compound heterozygote) |
| Symptoms | Usually none; may have mild anemia | Severe anemia, pain crises, organ damage |
| Treatment Need | None | Lifelong transfusions, chelation, or curative therapy |
| Risk to Offspring | If partner is also carrier, 25% risk per pregnancy | If partner is carrier, 50% risk of carrier, 25% risk of disease |
What This Means for You
None of this changes the most important fact: the moment where prevention is actually possible is before conception, not after. A carrier screening test is simple, requires no special preparation, and gives a couple—or an individual planning marriage—clear, actionable information at a point where it still changes the outcome.
If you're planning marriage, planning a pregnancy, or simply come from a community or family history where these conditions are more common, a genetic carrier screening test is one of the most consequential health decisions you can make before, rather than after, the fact. DNA Labs India offers dedicated gene-level panels for both conditions — a comprehensive alpha and beta thalassemia gene panel, individual beta-thalassemia and alpha-thalassemia mutation analysis tests, and sickle cell options ranging from NGS-based HBB gene testing to targeted mutation detection and mutation screening panels — so an informed decision, not chance, decides your family's future.
Frequently Asked Questions
1. What is the difference between a thalassemia carrier and thalassemia major?
A carrier (thalassemia minor) has inherited the faulty gene from only one parent and is usually healthy with no symptoms. Thalassemia major means both gene copies are affected, causing severe anemia from early childhood that requires lifelong blood transfusions and iron-chelation treatment.
2. Can two thalassemia or sickle cell carriers marry each other?
Yes, there's no legal restriction, and many carrier couples marry without complications. The key is awareness: if both partners are carriers of the same disorder, each pregnancy carries a 25% chance of an affected child, so genetic counseling before conception allows the couple to make an informed choice.
3. Is premarital thalassemia and sickle cell screening mandatory in India?
No. Unlike some Gulf countries, India does not currently have a nationwide mandatory premarital screening law. Screening happens through national missions like the National Sickle Cell Anemia Elimination Mission, state pilot programs, and individual choice—not legal requirement.